Silicone versus saline breast implants in Australia
A practical comparison of silicone gel and saline implants for Australian patients: feel, rippling, rupture behaviour, TGA listings and what a Sydney consult should cover before you choose a fill.
· Updated · 6 min read
In most Sydney consulting rooms the choice between silicone and saline is no longer a fifty-fifty fork. Cohesive silicone gel dominates private lists, and many patients arrive already assuming that “gel” is the grown-up option. That assumption is not always wrong. It is incomplete. A fill is a device, a rupture story, a surveillance plan and a set of compromises with your own tissue — not a personality type.
This journal rebuilt a vanished clinic domain as an editorial publication. We do not sell either device. We do describe, in Australian English, what the two fills actually do once they leave the tray.
What each device is filled with
A saline implant is a silicone elastomer shell filled with sterile salt water, either pre-filled or filled in theatre through a valve. The fluid is the same class of fluid used in drips. If the shell fails, the body absorbs the saline and the breast loses volume, usually obviously and within days.
A silicone implant is a silicone shell filled with a cohesive gel. Modern gels are designed to hold a shape if cut on a bench. They are not water. They are not liquid oil in the 1990s sense that still haunts family stories. If the shell fails, the gel may stay inside the capsule that the body has already formed, or it may travel locally. The breast may keep its size. That is why rupture can be silent.
Both devices are foreign bodies. Both require a shell. Both sit under Australian device regulation. The difference that patients feel in a fitting room — “this one is squishier” — is real, and it is not the whole story.
How they sit on an Australian chest
Sydney summers are unkind to denial. Swimwear, linen shirts and air-conditioning reveal rippling that a winter jumper hid. Saline, because it is water in a bag, transmits folds more readily, especially in the upper pole and along the cleavage when cover is thin. Silicone gel dampens those folds. It does not abolish them. People with very little subcutaneous fat, or who choose a large implant relative to their footprint, will see or feel edges with either fill.
The other tactile difference is motion. Saline can slosh; some patients like the honesty of that, most do not. Gel moves as a mass. “Natural” is the word clinics reach for. A more precise word is damped. Whether that looks like your own breast depends on your skin, your pec, your nipple position and whether a lift was needed and skipped.
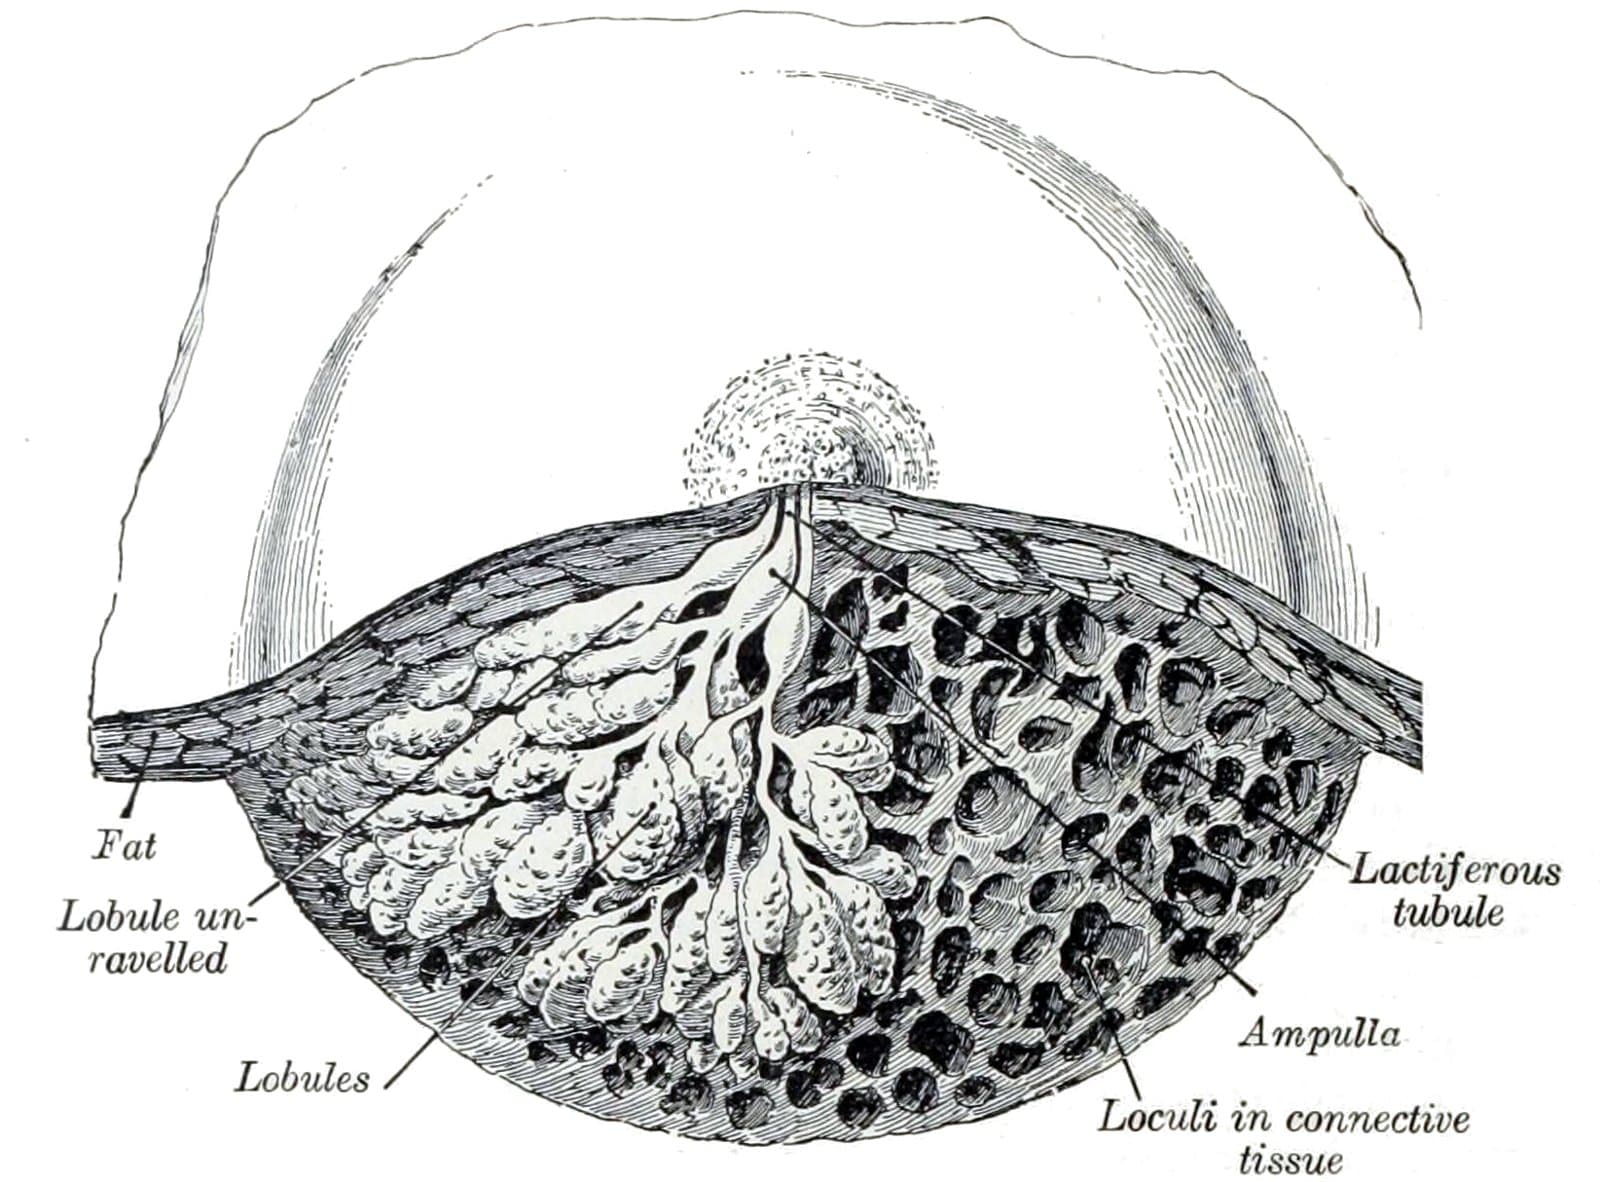
If you want a sense of the anatomy the implant is negotiating — gland, fat, muscle, fold — the public-domain plate we use on this hub is a reminder that the device is a guest in a layered organ, not a decoration on a flat wall. Read it beside our essay on implant profiles and projection.
Rupture, silence and what you do next
Saline rupture is a social event. One side goes down. You call the rooms. You are not guessing. The downside is that you have a deflated breast in public while you wait for a list.
Silicone rupture is a paperwork event first. Australian surgeons will talk about the Australian Breast Device Registry, about ultrasound, about MRI when the picture is unclear. The Therapeutic Goods Administration has, over the past decade, treated breast implants as devices that require ongoing vigilance, not as set-and-forget cosmetics. That culture is why a responsible consult in New South Wales now includes a sentence about how you will look for failure, not only if.
Neither fill is maintenance-free. Warranties from manufacturers are not the same as a promise that you will never have theatre again. We unpack that bargain in implant warranties, rupture and surveillance.
TGA listings, textures and the company you keep
Fill is not the only variable the TGA watches. Surface — smooth versus textured — became a public story because of breast implant-associated anaplastic large cell lymphoma. Many of the devices withdrawn or restricted in Australia were textured silicone implants, not saline bags. If you are comparing fills, you are also comparing the surfaces and brands still lawfully supplied. See implant surfaces, texture and the TGA landscape before you treat a brand name as a lifestyle.
Saline devices were never the centre of the ALCL story. That does not make them automatically “safer” in every other sense. Infection, malposition, capsular contracture and disappointment are equal-opportunity problems.
Cost, theatre time and the quote on the page
In Sydney, the implant is rarely the largest line on a private quote. Surgeon fee, assistant, anaesthetist, hospital and garment usually dwarf the difference between a saline and a silicone pair. Where fill does change money is in revision: a silent silicone rupture found on imaging is a planned day; a saline deflation is an urgent aesthetic emergency that still needs a list.
Some patients ask for saline because they want a smaller scar and a fill-in-theatre trick that lets the surgeon adjust volume. That trick is real and limited. You cannot negotiate your way out of thin tissue with a valve.
For the wider bill, read what breast implants cost in Sydney.
How a thorough consult should talk about fill
A consult that only asks “silicone or saline?” is selling a catalogue. A consult that earns the fee will ask about breastfeeding plans, mammographic screening, gym habits, how you feel about a possible silent rupture, how you feel about a public deflation, and whether you already have imaging of cysts or asymmetry. It will say which devices the surgeon actually uses and why others are off their tray.
You should leave knowing:
- which fills that surgeon places in a month, not in a brochure
- what surveillance they recommend at three, five and ten years
- what happens to the quote if a device is back-ordered
- how they manage a rupture on a Friday afternoon in February
If those sentences do not appear, the gap is not your lack of research. It is the consult.
Who still chooses saline, and why that can be rational
A small group of Australian patients still prefer saline: people who want an immediate, visible sign of failure; people with a strong family story about 1990s gel; people having a simple augmentation where rippling is unlikely because they have adequate cover; people whose surgeon prefers the intraoperative volume adjustment. Rational is not the same as fashionable. Fashion is not a surgical indication.
A larger group will be steered to silicone because the surgeon believes the feel and the rippling profile will match the goal. That steering should still be explained, not implied.
What this journal will not tell you
We will not tell you which fill to buy. We will not pretend a cohesive gel is organic. We will not pretend saline is old-fashioned and therefore honest. We will say that both are industrial products sitting under an Australian regulator, that both can look excellent, and that both can look like a mistake if the plan ignores your tissue.
If you are earlier than the fill question — still deciding whether surgery is the right verb — start with what a thorough Sydney consultation includes and how to choose a FRACS plastic surgeon in Sydney. If you are past fill and into shape, continue to anatomical versus round implants.
The useful question is not “which implant is best?” It is “which failure mode, which feel and which surveillance plan can I live with in this city, in this climate, in this body?”
This article is independent editorial information for a general Australian audience. It is not medical advice, not a diagnosis, and not an advertisement for a health service or a particular practitioner. Decisions about surgery belong with you and an AHPRA-registered specialist who has examined you. See our editorial standards.
Questions readers send the desk
- Are saline implants still available in Australia?
- Yes, but they are far less commonly placed than silicone gel devices. Availability depends on the surgeon's preferred suppliers and on current TGA listings.
- Which fill looks more natural on a slim chest?
- Cohesive silicone usually hides less gracefully than people hope on very thin cover, but it still ripples less than saline. The cover of tissue matters more than the marketing adjective.
- If a silicone implant ruptures, will I know immediately?
- Often not. Silent rupture is one reason Australian surgeons discuss ultrasound or MRI years after placement, not only when something feels wrong.